




Cystitis
Cystitis is a common type of urinary tract infection (UTI) affecting your bladder. It’s usually caused by a bacterial infection. Cystitis is usually treated with a short course of antibiotics, though mild cases can be managed at home.
About cystitis
You usually get cystitis when bacteria enter your bladder through your urethra (the tube that carries urine out of your body). This can happen if bacteria from your back passage (rectum) or vagina spread to the opening of your urethra.
Bacteria can also enter your bladder directly. This may happen during surgery on your bladder or if you have a catheter (a tube that’s put into your urethra to drain urine out of your bladder). The bacteria may also come from your bloodstream.
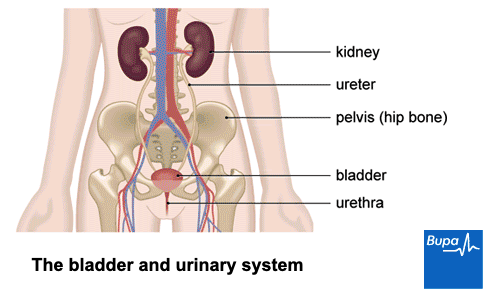
Women are more likely than men to get cystitis. This is because the urethra in women is closer to the back passage than in men. So bacteria don’t have as far to travel to reach the bladder. In women, the urethra is also shorter. The urethra entrance is also close to the vagina, which is why women may get cystitis after sex. Around half of women will get a urinary tract infection such as cystitis at some point in their lifetime. Older men are more likely to get cystitis than younger men.
Bladder Health
Bladder Health | Watch in 23:52 minutes
Dr Zoe Williams and Bupa’s Dr Elizabeth Rogers speak honestly about urinary incontinence, overactive bladders, pelvic floor issues and more.
Welcome to Inside Health where we help you get under the skin of some of the big health concerns that affect us all. Today we're shining a light on bladder health, so we're going to be talking about some of the common bladder conditions, giving you some top tips on how to manage your pelvic floor, and answering some of your questions.
There was a recent Bupa survey that found 64% of respondents said bladder issues were among their biggest concerns, so it’s a really topical issue. I’m delighted to be joined by Dr Lizzie Rogers, who’s a fellow GP and Associate Clinical Director at Bupa, to uncover some of those conditions that people think they’re just supposed to live with. They don’t realise there’s so much we can do to help them, and we’ll also answer some of those questions that people find too embarrassing to ask.
So I think let's start off with talking about urinary incontinence. As GPs, that is definitely the commonest bladder issue that we face. What exactly is urinary incontinence?
Yeah. Urinary incontinence is essentially the involuntary leakage of urine. By that, I mean you go for a wee when you don’t want to or don’t intend to, and it can vary from just a few tiny drops to much larger volumes.
And there are different types of urinary incontinence as well, aren't there?
Yeah, so there are two main types. So you have stress incontinence, and that typically tends to be when you leak a bit of urine when you either cough or you exert yourself or sneeze—so anything that's raising the pressure in your abdomen and it presses on your bladder and you leak a bit of urine out.
And urge incontinence is when you get the sudden urge to go to the toilet and you have to go then and there, so you can't hold it, you haven't got time to get to the toilet. And you can actually have mixed incontinence as well; so that's when you typically tend to have some symptoms of stress incontinence and some symptoms of urge incontinence. And usually, what we tend to do in those situations is figure out which symptoms are causing you more bother, and then we'll try to treat that kind of incontinence first.
And I think that’s the key thing, isn’t it? We can treat both types, and there are lots of different treatments for each. Yet I hear it all the time. Ladies come in for something else and, if I ask them about urinary incontinence, they say, “Oh yeah, I leak a bit of urine, but who doesn’t at my age?” Actually, that’s the big issue: people just accept it when there’s so much we can do to help. So what are some of the typical causes of urinary incontinence?
So the causes depend on which type of incontinence you've got, and often we don't find one single cause, so it tends to be kind of multifactorial. If we think about stress incontinence—so this is the kind where you leak a bit of urine when you either cough or sneeze or exert yourself—we need to have a bit of a think about the structures involved when you need to urinate. So we've probably all heard of our pelvic floor—so a group of structures and muscles that basically help control the flow of urine out of the bladder. Anything that either weakens or damages these muscles can lead to incontinence.
So you might think about things like pregnancy, having a vaginal birth—having a forceps delivery, for example, can damage the pelvic floor. Having constipation, so you're having to strain a lot, or having a chronic cough where you're coughing all the time—so those can all be causes.
Urge incontinence is slightly different, as we've already talked about. So in urge incontinence, it's when you get the sudden urge to go then and there, and your bladder suddenly contracts and you think, "Gosh, I've got to go to the loo." And this can often develop as you get older—that's kind of just part of the physiological makeup of getting older—and it can sometimes occur after certain neurological conditions which affect the nerves supplying the bladder, so that might be something like a stroke.
Lifestyle factors are really important as well. Caffeine tends to irritate the bladder, so you may find that drinking a lot of it can cause problems. Other factors include drinking alcohol, having a urine infection and taking certain medications.
And I think it's really important to mention that urinary incontinence can affect people of all ages, even though we tend to think of it as something that affects older people. And that's important so that people who are younger who are having issues know they can come forward and speak to the GP and get help. But it is commoner as we get older, isn't it?
Yeah, absolutely. And that's because of certain physiological changes in our bodies as we get older, which means we're more likely to develop incontinence. But also alongside that, we're more likely to develop certain conditions such as diabetes, which also predisposes to incontinence.
Commonly we think of it affecting women more, but tell us some of the reasons why it might impact on men?
Yeah, so men do also have a pelvic floor as well. So ensuring that they've got a strong pelvic floor and avoiding things like a chronic cough and constipation are really important. Our anatomical makeup is, of course, slightly different. So in men, you've got the prostate gland, and that sits just below the bladder. Urine comes out of the bladder through a tube called the urethra, and that passes through the middle of the prostate gland. If there are changes in the prostate gland, such as it getting large, that can press on that tube and it can affect the way that urine flows out of your bladder. So it can cause problems such as a weak stream—it makes it harder for men to go to the toilet—but for many men, they also get problems with urge incontinence and urgency and feeling like they need to go to the loo then and there or that they need to go to the toilet really frequently.
Okay, so really important—you know, it can actually affect anybody. Having said that, it absolutely is more common in women. And what are some of the reasons for that?
Yeah, so we've touched on a couple of them already. So pregnancy and childbirth is a big one; so that can cause damage to or weaken some of those muscular tissues around there. And certainly later in life as well—so as women come up to the menopause, so the perimenopause period and then sort of postmenopause period—you see changes in the hormone estrogen, and typically it tends to fluctuate and then it kind of drops off. Estrogen's really important in kind of maintaining the structure and integrity of the tissues in the vagina and the bladder—and the bladder wall, in fact. So as your estrogen level drops off, all those structures can become weaker, and women may find that they experience incontinence symptoms then.
I think something important to raise around this is symptoms linked to the menopause. We know that HRT is the gold standard treatment for menopausal symptoms; however, lots of people can't take HRT or choose not to. But there is an option of using topical estrogen for a lot of these symptoms we're talking about—genitourinary symptoms—that can be highly effective. And topical estrogen doesn't have a lot of the risks associated with other types, and you can actually buy it over the counter. So I think that's important to let people know as well.
I think for anybody experiencing urinary incontinence, it can have such an impact on their life, on their health, on their social life, on what they do, even the clothes that they wear. So what would you advise people to do if they are experiencing this?
It’s so important, isn’t it? It really does affect your physical life, but also your mental health and your relationships. It can affect how you feel about sex, for example. So it’s important not to suffer in silence. There’s so much your GP can do, and there’s a lot you can do through lifestyle changes as well. If you’re having problems, speaking to your GP is an excellent first port of call.
Excellent. Well, thank you so much for sharing that. I think that's really, really useful information. We've got some top tips coming up next on how to manage your pelvic floor, so do stay tuned for that.
When it comes to bladder health, one of the most important things for us to talk about is how to train your pelvic floor. I think looking after your pelvic floor is one of the best ways that we can prevent issues like incontinence in the future, but it also forms a really important part of the treatment plan if people are having issues like incontinence.
So here are my top tips for looking after your pelvic floor: Firstly, I think it's important to identify what the pelvic floor is. It's a structure that's deep in the pelvis that's made up of muscles and connective tissue, and you can kind of think of it as a trampoline that attaches at the front on the pelvic bone, at the back on the tailbone, and either side on the seat bones. And you want that trampoline to be firm and strong but have a little bit of give, like a good trampoline.
On top of that trampoline sits your bladder, your womb (if you're a woman), and your bowels. And there are some holes in it, and these holes allow you to pee and poo. When you jump up and down, for example, or cough or sneeze, those muscles give a little bit of tension to maintain control of the bowels and the bladder. So pelvic floor exercises are what are important to keep it healthy and keep it strong.
And the good news is that you can do these just about anywhere and just about at any time. So they take about 2 minutes—so you could do it whilst you're waiting for the kettle to boil, whilst you're waiting for your toast to pop up, or even whilst you're just running some water to do the washing up. Ideally, you should do them three times a day.
Next, I’m going to describe exactly how to do a pelvic floor exercise. It’s a bit complicated, so I’ll take you through it step by step and do it with you. I want you to follow along with what I do.
Okay, first of all—just go with me on this—imagine you need to fart but you're in a busy lift and you need to hold on to it. So just imagine that, and what I want you to do now is hold on to the fart. So the muscles you're using are part of the pelvic floor. Relax them. Now what I want you to do is do that again: Imagine you're going to fart, hold on to it, and pull those muscles up inside and hold on to them. Well done; that's the first bit.
The next bit is imagine you're having a pee and somebody's walking in the room and you don't want them to know you're there, so you need to stop midway through. So imagine you're having a pee, hold on to it, stop it—and relax. Then we'll do that one again: Imagine you're having a pee, stop it, pull those muscles up inside, squeeze—and relax.
And the relaxation part is really important as well. Some people have what we call a hypertonic pelvic floor, and that's when the trampoline is a bit too taut because they're clinging onto those muscles all day long. What tends to happen in that scenario is that they get tired as the day goes on, and people might notice that they have issues with bladder control later in the day, for example.
Okay, so now you've got all the different components, we're going to put it all together to do one exercise. So first of all, imagine you need to fart, hold on to it, draw it up inside. Imagine you need to pee, hold on to it, draw it up inside. You should relax your buttocks, relax your legs—it should be just the muscles inside. Squeeze for as long as you can—and then relax. You'll only be able to hold on to it for one to two seconds at the start, but that will get longer as you progress.
So you just did one exercise. Well done! You do eight of those three times a day, and that is the ideal workout for your pelvic floor. I know it's a lot to remember, but there are things out there to help. So the Squeezy app is amazing—gives you daily reminders to do your exercises and guides you as to how to do them. So that's great for both men and women. There are also lots of devices out there for women to use that you insert into the vagina—so Kegel weights—as well as lots of new electronic devices that are coming on the market all the time. So do check those out and see what's going to work for you.
And remember, you know, we all have a pelvic floor, we all should be exercising, and if you are somebody who's having symptoms such as incontinence, then stick with it. It can take a while before these exercises kick in, but after a couple of months, you should have noticed a benefit.
Now another really common condition that people struggle with is overactive bladder, which is a different condition to incontinence, but there can be a lot of overlap in symptoms. So I'm back with Lizzy to take a look at this issue. So Lizzy, let's start then by explaining what we mean by an overactive bladder.
Yeah, so your bladder is essentially a big muscular bag, and it fills up with urine during the day. When it gets to about half full, that's typically when you would get the sensation or the urge to want to go to the toilet, and most of the time we would wait until it's a convenient time to do that. Now, with an overactive bladder, what it tends to do is it fires off—so it misfires those signals and it does it before it's half full, usually.
And then, I guess, you don’t have the opportunity to get to the loo. The bladder starts to contract and, before you know it, the urge to pass urine is very strong.
Yeah, absolutely. And in some people, it can be so severe that it actually causes incontinence—they just haven't got the time to go to the loo. In other people, as you've said, they get this urge, this real, real sense of needing to go, and they have to go very quickly. And for many people, because it's happening so often, it means they need to go to the loo a lot during the day, which can be really bothersome. And then, in fact, for some people actually, it can cause problems overnight as well as the daytime. So rather than kind of getting up to go once or twice at night, they might find that they're having to get up several times overnight.
So what are then the main symptoms of overactive bladder?
Yeah, so there are four main symptoms. One of which you kind of highlighted, which is what we call urgency—so that's when you feel you've got to go then and there and it's a really strong urge. Many people also find that they suffer from something called frequency, and by that we mean that they've got the urge to go not only very quickly but, for many people, several times a day. So they might feel like they're constantly making trips back and forth to the loo. And for some people, actually, that can extend into the night, and we have what's called nocturia, and that means you're having to get up several times during the night to go to the loo, which is just exhausting. And then finally, for some people, it can be so severe that actually they have incontinence—they just haven't got the time to go to the loo or get there on time because the urge is so, so strong.
I mean, there's some really distressing symptoms in there that I think can have a huge impact on people's lives. What are some of the causes?
So in most cases, we don't actually necessarily know exactly what the cause is, and for those people, we tend to call it overactive bladder syndrome. Now for other people, we may have a specific cause that we can identify, and that tends to be conditions that either affect the brain or affect the nerves supplying the bladder. So that might be something like a stroke or in Parkinson's disease, in conditions like multiple sclerosis, or if they've had an injury to their spinal cord, for example. And we don't call it overactive bladder syndrome in these people.
And are there any other more sort of common everyday conditions that this could be a sign of?
Yeah, absolutely. Certain chronic conditions, such as diabetes, can cause these symptoms, as can a urinary tract infection. Pressure from outside the bladder can also be a factor. For example, if you’ve got lots of fibroids in your uterus, which lies very close to your bladder, that can cause symptoms. If you speak to your GP, they’ll often want to do further tests to investigate and rule out these causes, such as checking for a urine infection. If they’re concerned about something outside the bladder, they might arrange a scan.
And does it affect both men and women? And what are some of the differences?
Yeah, so absolutely, it does affect both men and women—it's not just women, which a lot of people, I think, commonly think. But due to our differences in our anatomy, the causes and how it presents can be different. So particularly thinking about men, they have a prostate gland. If you've got problems with your prostate gland, that can cause problems with the urethra and then pressure in the bladder as well.
I think again this is a condition that can really be disruptive to people's lives, particularly if they're having to plan their day around being close to the loo, if they're not getting great sleep at night because they're up during the night, especially if they are, you know, having leakage and incontinence. How would you advise people if they are experiencing these symptoms?
Yeah, I mean, I'm sure we've all experienced how terrible we feel after a poor night's sleep, right? It's just rubbish. And you know, it really affects your physical well-being as well as your mental and the impact on relationships. But there's so much that can be done about it, both from a lifestyle perspective and kind of from a medical perspective. So I would really encourage people not to suffer in silence—go and speak to your GP, because I'm sure there's something that can be done to help.
Yeah, and we mustn’t normalise it. It’s not normal, and there are lots of things we can do to help. So, as you rightly say, don’t suffer in silence. I think what people really want to know at this stage is: what can they actually do? There are lots of things they can do. What are your top tips and advice for managing these symptoms?
Absolutely. So as you demonstrated earlier, Zoe, pelvic floor exercises are really important. There's a great app called the Squeezy app, which is really useful—it helps you set reminders, it talks you through how to do them. I used it in my pregnancies and it was brilliant, really helpful.
Reducing your caffeine intake is another good place to start. Caffeine irritates the bladder, and it's also what we call a diuretic—and by that, what I mean is it encourages the body to produce more urine. So it really has this double whammy effect. Coffee tends to be the biggest culprit; however, there are other sort of caffeine-containing drinks such as fizzy drinks, tea, and hot chocolate, and even chocolate itself. And in fact, some cold and flu relief medications have caffeine as well, so it's worth being aware of that.
If you're overweight, trying to lose some weight can help—it reduces the pressure on your pelvic floor. And making healthy lifestyle choices such as reducing your alcohol intake and, if you're a smoker, now is a really good time to think about quitting smoking.
In some cases, if that's not working, your GP might consider referring you on for some further input with a physiotherapist or a continence advisor. And what they do is something called bladder retraining, and it's basically a way of helping you regain control over your bladder.
Okay, that’s really useful, thank you. I think there are tips for everybody there. The key message is that, if those lifestyle measures don’t make a difference, don’t suffer in silence. These bladder symptoms aren’t a normal part of ageing, and there are so many things that can be done to help. If in doubt, please make an appointment and speak to your GP.
So in these final few minutes, we've had so many questions submitted before the event, but I've picked out a few that we haven't naturally covered in the questions and answers so far. First one is: "I get recurrent UTIs (urinary tract infections). What can be done to prevent this?"
So when we talk about UTIs, we tend to refer to what we call cystitis, which is an infection in the bladder. And they can be really bothersome and really uncomfortable. And there's lots of different things that can cause them: constipation, being pregnant, diabetes, being dehydrated, having prostate problems—and some people even experience frequent UTIs after they have sexual intercourse.
Menopause as well.
Menopause as well, exactly. But there are lots of things you can do to help prevent UTIs: keep well hydrated and drink plenty of fluid throughout the day. If you get the urge to go to the loo, try not to hold it for too long, because keeping urine in the bladder increases the chance of an infection. Go to the toilet after sexual intercourse to help flush out any bacteria. Avoid constipation by eating plenty of fruit and vegetables and getting enough fibre in your diet. Maintain good hygiene—for example, if you’re a woman, wipe from front to back. If you’ve got a chronic condition such as diabetes, make sure you attend regular reviews with your GP and that it’s well controlled. All of these things can help.
Brilliant, great, some wonderful tips there. The next question is: "I get up every night and go to the toilet two to three times. Is this normal?"
Yeah, so great question. So typically we tend to say that it's within normal limits to urinate once at night, and if you're urinating more than that, it's worthwhile having a think about why that might be. And there can be various lifestyle things that can cause it: If you're drinking caffeine—a lot of caffeine—you know, we've talked about it already, all the different kind of drinks that contain it. Also if you're drinking alcohol late at night, that can cause you to get up. For men, they might have problems with their prostate, for example—it's getting larger, it can make it harder to wee so that you end up having to go lots but often, and that can cause you to get up and go to the loo at night as well.
Okay, so that’s really key. Try a few of those lifestyle changes, but if you’re consistently getting up more than once a night, it’s worth seeing your GP.
Next one: "I have a weak stream when going for a wee. Why is this?"
Yeah, so often we see men coming in and talking about having a weaker stream, and that's really usually due to problems with the prostate. So as we talked about before, because of the position it sits in below the bladder, it presses on the urethra where the wee comes out of, and it causes back pressure into the bladder and it narrows that tube effectively. So what you find is it's harder to push it out, and when it does come out, the stream isn't good. I kind of think of it a bit like a garden hosepipe. So for those men, they can find it's much harder to go, and also what they can find is that towards the end of urinating, it tends to kind of dribble at the end—so it gets slower and slower and trickles off. They may also find that they go and then they feel like they need to go back again as well.
The good news again with prostate problems—if you're getting symptoms like that—is there's lots that can be done about it as well. So don't suffer in silence; see your GP. They'll probably want to do some further tests to investigate the cause, but there's medications and all sorts that can be done to improve those symptoms.
And sometimes if that obstruction around the urethra gets worse and worse and worse, it can get to the point where the bladder can't empty—they can't push against them—and we call that urinary retention. What happens then?
Yeah, exactly. You can’t empty your bladder properly. It tends to be very uncomfortable and painful. At that point, we need to get you into hospital—or your GP surgery, if they offer the procedure—to have a catheter inserted. That’s a tube that helps drain the urine. The good news is that it usually doesn’t stay in permanently; it’s a temporary solution while clinicians start medication or consider other ways to relieve the pressure from the prostate.
Sadly Lizzy, that's all we have time for, but thank you so much. I think that information you shared with us has been absolutely brilliant. And thank you to you for joining us as well. We really hope that today's been informative, it's given you some tips, some advice for lifestyle changes if you are having symptoms—but more than anything, we hope that it's reassured you that these types of symptoms are not normal. There's loads that can be done, so please do make an appointment with your GP if you're struggling.
Types of cystitis
You may hear different terms used to describe cystitis.
- Your doctor may just call it a UTI (urinary tract infection) rather than cystitis. An uncomplicated UTI is when you don’t have any other underlying health problems increasing your risk of complications. The infection usually clears up easily by itself or with antibiotic treatment. It doesn’t cause too many problems.
- A complicated UTI means you may have other health conditions that can make the infection more dangerous for you. It may be harder to get rid of the infection, or you may be at greater risk of complications.
- A recurrent UTI is when your infection keeps coming back. It usually means you’ve had three or more episodes within six months.
Sometimes you can have symptoms of cystitis without any signs of a bacterial infection. This is called interstitial cystitis, or painful bladder syndrome. Interstitial cystitis is a different condition. It may be caused by a problem with your bladder or immune system, or changes to your nervous system.
Causes of cystitis
Cystitis is caused by a bacterial infection. Around 8 in every 10 cases of cystitis are caused by bacteria called Escherichia coli (E. coli). These bacteria usually live harmlessly in your bowel or vagina.
Certain things can increase your risk of developing cystitis. These include the following.
- Having sex. Bacteria from your vagina or back passage may get into your urethra when you have sex.
- Having a new sexual partner in the last year.
- Conditions that affect the structure of your urinary tract or how it works. This may make it easier for bacteria to enter your bladder.
- Not being able to completely empty your bladder. In men, this is often due to an enlarged prostate.
- Pregnancy. Pregnancy hormones and your growing uterus make it harder to empty your bladder when you’re pregnant. This can make UTIs more likely.
- Taking antibiotics, especially regularly. These medicines can increase the growth of E. coli bacteria in your vagina.
- Having a weakened immune system. Anything that weakens your immune system – including type 1 and type 2 diabetes and HIV – can increase your risk of infection.
- Menopause. Low oestrogen levels can make your urethra wall thinner. This can make you more prone to cystitis.
- Having a catheter. Your risk of cystitis increases the longer you have the catheter. Other procedures or surgery on your urinary tract also increase risk.
- Some types of contraception. Using a diaphragm or spermicide-coated condoms may make you more likely to get cystitis.
- Stones (calculi) in your urinary system – kidney stones or bladder stones. These can trap bacteria, causing an infection.
If you’ve already had cystitis, your risk of getting it again is higher. This is even more likely if you had it as a child.
Symptoms of cystitis
Typical symptoms of cystitis include:
- burning or stinging when you pee
- needing to pee regularly, but only passing a little urine
- needing to pee more often at night
- a strong urge to pee – this can cause incontinence (peeing without meaning to)
- cloudy, dark or strong-smelling urine
- blood in your urine – you may not be able to see the blood, but it can be picked up in urine tests
- pain in your lower tummy
You may get more general symptoms, including:
- tiredness or feeling generally unwell
- a high temperature (fever)
- feeling or being sick
- feeling confused (especially in older people)
Some people may have these general symptoms without the typical symptoms of cystitis. But these symptoms may also be a sign of a kidney infection (pyelonephritis). If you have these symptoms, it’s important to speak to your GP surgery. You should also contact your GP if you have new vaginal discharge or more vaginal discharge than usual. Your symptoms may be caused by a vaginal infection rather than cystitis.
Sometimes, you may not have any symptoms at all with cystitis. You may only find out you have the infection if you have a routine urine test for another reason.
Cystitis in children
Children with cystitis may have symptoms similar to adults. Their symptoms may include:
- pain when they pee
- peeing more often
- wetting the bed
- urine with a bad smell
Younger children and babies may be more likely to:
- have a high temperature
- be sick (vomit)
- be irritable
- not want to eat or feed
Cystitis symptoms can come on very suddenly. They may be so bad that you find it hard to do your usual activities.
Seeking help for cystitis symptoms
Cystitis normally clears up on its own. But your local pharmacist can give you advice on managing your symptoms. If your symptoms aren’t starting to get better after a few days, you should see a GP.
Most pharmacies in the UK can test you for cystitis and prescribe antibiotics if you have a bacterial infection. You may be able to talk to your pharmacist about cystitis treatment rather than seeing a GP if the pharmacy offers the Pharmacy First service. The pharmacist may prescribe a three-day course of nitrofurantoin (an antibiotic) for cystitis. If a pharmacist prescribes antibiotics but the medicine isn’t working after 48 hours, it’s important to go back to the pharmacy or see your GP.
It’s important that you see a GP straight away if you:
- can see blood in your urine
- are male and you have any UTI symptoms
- think your baby or child may have cystitis
- are pregnant and think you may have cystitis
- keep getting infections, despite trying self-help measures
- have other long-term illnesses that affect your immune system, such as diabetes
- are feeling very unwell with a temperature or shivers, pain in your sides, or vomiting
- have unusual or increasing vaginal discharge
Diagnosis of cystitis
Your GP will ask about:
- your symptoms
- your medical history
- whether you could be pregnant and if you use contraception
- which treatments you have already tried, including antibiotics from a pharmacy
They may also ask to examine you.
Your GP will often be able to diagnose cystitis from your symptoms without doing any tests. They may ask for a sample of your urine to check for signs of a bacterial infection. Sometimes, they may send the sample to a laboratory for further tests.
Most people won’t need any further tests. But sometimes your GP may recommend further tests to check for any underlying problems, especially if your cystitis keeps coming back. Tests may include:
- an ultrasound scan of your kidneys and bladder – this uses soundwaves to create an image of the inside of your body
- a cystoscopy – this is a test to look inside your bladder and urinary tract using a thin tube inserted into your urethra
If you have symptoms of cystitis but you don’t have signs of a bacterial infection, you may have interstitial cystitis. Interstitial cystitis is difficult to diagnose and treat, so your GP may refer you to a specialist for further investigation.
Self-help measures for cystitis
Mild symptoms may clear up after a few days without any specific treatment for cystitis. In the meantime, you can try the following to ease your symptoms.
- Take over-the-counter painkillers such as paracetamol and ibuprofen to help with any pain.
- Drink enough fluids to keep hydrated.
- Don’t drink too much strong tea or coffee (containing caffeine), alcohol, or acidic drinks (such as fruit juices and fizzy drinks).
You can buy cystitis remedies over the counter from a pharmacy. These aim to make your urine less acidic and reduce the burning or discomfort when you pee. But there’s no evidence that these cystitis sachets work. If you decide to try them, check with your pharmacist or GP first. You may not be able to use them if you’re pregnant, on a low-salt diet, or have heart, liver, or kidney problems.
There’s no evidence that cranberry drinks or products help to relieve cystitis symptoms.
GP Subscriptions – Access a GP whenever you need one for less than £20 per month
You can’t predict when you might want to see a GP, but you can be ready for when you do. Our GP subscriptions are available to anyone over 18 and give you peace of mind, with 15-minute appointments when it suits you at no extra cost.
Cystitis treatment
Your GP may prescribe antibiotics for cystitis. Sometimes you may have a delayed prescription. This means you only start the antibiotics if your symptoms don’t get better within 48 hours – or if they start getting worse. If your GP doesn’t think you need antibiotics, they’ll talk to you about self-help measures (see the above section).
You usually take antibiotics for cystitis for three days, but sometimes they’re prescribed for seven days or longer. Your symptoms should start to ease after a couple of days of taking antibiotics. If they don’t, you should see your GP again. Your GP may send a sample of your urine to a laboratory to check which bacteria are causing your symptoms. They may then prescribe a different antibiotic.
It’s important to take the whole course of antibiotics, even if your symptoms seem to have cleared up. Always read the patient information leaflet that comes with your medicine. If you have any questions, ask your pharmacist or GP for advice.
If your cystitis comes back or the antibiotics still aren’t working, see your GP. They may refer you to a urologist (a doctor who specialises in the urinary system) or a urogynaecologist for more tests.
Complications of cystitis
Cystitis is usually mild and doesn’t cause any further problems. But in some people, it can be harder to get rid of or more likely to cause complications. Certain things can make you more likely to develop complicated cystitis.
These include:
- being pregnant
- being older
- getting cystitis from a catheter
- having conditions that affect the structure or your urinary tract or how it works
- having conditions affecting your immune system, such as diabetes
The most common complication is when bacteria from your bladder travel up to your kidneys. This causes a kidney infection (pyelonephritis). Symptoms can include pain in your side and back and a high temperature (fever). You may feel sick (or be sick) too. Pyelonephritis can be treated with antibiotics. If it isn’t treated, it may damage your kidneys.
If you’re pregnant, untreated pyelonephritis can cause you to give birth early. You’ll be screened for cystitis at your early antenatal appointments. This means if you have it, it can be treated quickly with antibiotics and reduce your risk of pyelonephritis.
Men are more likely than women to develop complications from cystitis. Cystitis in men may lead to an infection of their prostate gland (prostatitis). This can cause pain, especially at the bottom of the penis and around the anus (back passage). Men may have difficulty passing urine. Prostatitis is treated with antibiotics.
Prevention of cystitis
If you keep getting cystitis, there are some things you can try to reduce the risk of it coming back. This includes the following.
- Drink enough fluids to keep hydrated.
- Eat a healthy, balanced diet to help your immune system work well.
- Wear underwear that’s made from natural materials, such as cotton or linen.
- Wipe from front to back after doing a poo.
- Always pee as soon as you feel you need to go – don’t put it off.
- Go for a pee as soon as you can after sex.
- If you’ve been through the menopause, consider using oestrogen replacement vaginal creams and gels.
- Try not to use spermicide-coated condoms or diaphragms.
Talk to your GP or practice nurse about the most appropriate contraception for you if you keep getting cystitis. Some people find that cranberry drinks or products help to prevent cystitis if they’re prone to the infections.
There’s some evidence that cranberry products can help prevent attacks in some people who get regular cystitis. Some people find that taking a substance called D-mannose helps with cystitis prevention. But there’s not a lot of evidence for D-mannose. If you’re pregnant, check with a pharmacist or your GP before taking these products.
Antibiotics to prevent cystitis
If you’ve tried the measures above and they aren’t helping, your GP may suggest taking antibiotics to prevent cystitis. This may be:
- a single dose to take when you’re exposed to something that usually triggers cystitis for you (such as having sex)
- a daily antibiotic
You’ll usually be prescribed trimethoprim or nitrofurantoin if you’re taking antibiotics to prevent cystitis. There are potential side-effects and risks to taking antibiotics regularly or long-term. Your doctor will discuss these with you.
Cystitis is usually caused by a bacterial infection. You usually get cystitis when bacteria enter your bladder through your urethra. Your urethra is the tube that carries urine out of your body.
For more information, see our causes of cystitis section.
The main symptoms of cystitis include burning or discomfort when you pee and needing to pee more regularly. This can include at night. You may have a strong urge to pee, and your pee may look cloudy.
For more information, see our symptoms of cystitis section.
Cystitis usually goes away by itself after a few days. If it doesn’t, a pharmacist or GP may prescribe antibiotics to help get rid of it. You usually take these for between three and seven days.
For more information, see our cystitis treatment section.
You don’t always need to see a doctor for cystitis. If your symptoms are mild, they may clear up on their own without any treatment. You can buy cystitis remedies from your local pharmacy to ease the symptoms. Most pharmacists can test your urine for bacteria and offer you antibiotics if you need them. But sometimes you should go straight to your GP, including if you’re pregnant or feel very unwell.
If you keep getting cystitis, it may help to make a few lifestyle changes. Make sure you’re drinking enough fluids. It may also help to make sure you wipe from front to back after doing a poo. Don’t hold off going for a pee when you need to, or after sex. Talk to your doctor about other possible options.
See our prevention of cystitis section for more information.
Did our Cystitis information help you?
We’d love to hear what you think. Our short survey takes just a few minutes to complete and helps us to keep improving our health information.
The health information on this page is intended for informational purposes only. We do not endorse any commercial products, or include Bupa's fees for treatments and/or services. For more information about prices visit: www.bupa.co.uk/health/payg
This information was published by Bupa's Health Content Team and is based on reputable sources of medical evidence. It has been reviewed by appropriate medical or clinical professionals and deemed accurate on the date of review. Photos are only for illustrative purposes and do not reflect every presentation of a condition.
Any information about a treatment or procedure is generic, and does not necessarily describe that treatment or procedure as delivered by Bupa or its associated providers.
The information contained on this page and in any third party websites referred to on this page is not intended nor implied to be a substitute for professional medical advice nor is it intended to be for medical diagnosis or treatment. Third party websites are not owned or controlled by Bupa and any individual may be able to access and post messages on them. Bupa is not responsible for the content or availability of these third party websites. We do not accept advertising on this page.
- Urinary tract infection (lower) – women. NICE Clinical Knowledge Summaries. cks.nice.org.uk, last revised February 2025
- Female urethra anatomy. Medscape. emedicine.medscape.com, updated March 2025
- Li R, Leslie SW. Cystitis. StatPearls Publishing. ncbi.nlm.nih.gov, last update May 2023
- Urinary tract infection in adults. Patient. patient.info, last updated March 2023
- Acute cystitis. BMJ Best Practice. bestpractice.bmj.com, last reviewed November 2025 https://bestpractice.bmj.com/topics/en-gb/298/epidemiology
- Bacterial urinary tract infections. The MSD Manuals. msdmanuals.com, last reviewed/revised January 2024
- Interstitial cystitis/painful bladder syndrome. Patient. patient.info, last updated February 2025
- Urinary tract infection (adult). The British Association of Urological Surgeons. baus.org.uk, accessed December 2025
- Menopause. NICE Clinical Knowledge Summaries. cks.nice.org.uk, last revised July 2025
- EAU guidelines on urological infections. European Association of Urology. uroweb.org, updated March 2025
- Urinary tract infection in children. Patient. patient.info, last updated August 2022
- Pharmacy First clinical pathways. NHS England. england.nhs.uk, updated September 2025
- NHS Pharmacy First Scotland. NHS Scotland. gov.scot, published April 2020
- Diagnosis of urinary tract infections: quick reference tools for primary care. Diagnostic decision tool for women (under 65 years) with suspected UTI. UK Health Security Agency. gov.uk, updated July 2025
- 26. Self help information for women with cystitis. The British Association of Urological Surgeons. baus.org.uk, published December 2025
- Urological pain. NICE British National Formulary. bnf.nice.org.uk, last updated November 2025
- Sodium bicarbonate. NICE British National Formulary. bnf.nice.org.uk, last updated November 2025
- Pyelonephritis. Patient. patient.info, last updated January 2022
- Urinary tract infection in pregnancy. The MSD Manuals. msdmanuals.com, last reviewed/revised July 2024
- Antenatal care. Patient. patient.info, last updated May 2025
- Prostatitis – acute. Diagnosis. Suspecting acute prostatitis. NICE Clinical Knowledge Summaries. cks.nice.org.uk, last revised June 2024

 Member help and support


