




Ulcerative colitis
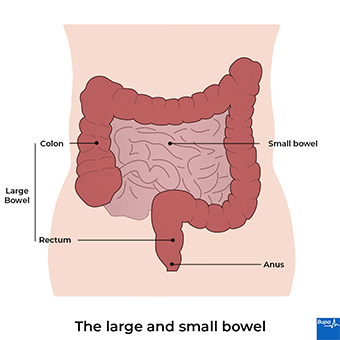
Ulcerative colitis is a long-term condition that causes your large bowel (your colon and your rectum or back passage) to become inflamed (red and swollen). This causes symptoms like diarrhoea (with blood in it), which may come and go, and tummy (abdominal) pain. There are lots of treatments to help control the symptoms of ulcerative colitis.
About ulcerative colitis
Ulcerative colitis is one of the main types of inflammatory bowel disease (IBD). The other is Crohn’s disease. In ulcerative colitis, the lining of your large bowel becomes inflamed, and can develop ulcers. If it affects only your rectum (the very end of your large bowel), it is called ulcerative proctitis. But it may spread upwards from here. The affected areas may bleed and produce mucus, which you then pass out when you poo.
Most people develop ulcerative colitis either between the ages of 15 and 30 or when they’re older at around 50 to 70. But you can get ulcerative colitis at any time in your life. Once you get it, you’ll usually have ulcerative colitis for the rest of your life.
Causes of ulcerative colitis
The exact cause of ulcerative colitis isn’t known. It’s thought that it’s probably an autoimmune condition in response to bacteria in your bowel. This means your body’s immune system attacks itself.
Ulcerative colitis runs in families. If you have a close family member with ulcerative colitis, you’re about four times more likely to develop it. Your chance of getting ulcerative colitis may also be affected by your environment and where you live. It’s more common in northern Europe, and in specific groups – for example, people of Ashkenazi Jewish descent.
Symptoms of ulcerative colitis
Ulcerative colitis symptoms usually come and go. This is called a relapsing and remitting pattern. Your symptoms can disappear (and you’re in remission), sometimes for years, before they come back again (flare-up, or relapse). Flare-ups can last anything from a few days to several months. You may feel well between flare-ups, with no symptoms.
During a flare-up, symptoms of ulcerative colitis may include:
- diarrhoea, often with blood or mucus in it – you may need to rush to the toilet, even at night
- lower tummy (abdominal) pain or cramps, which may go away after you’ve had a poo
- feeling like you still need to go for a poo even when there’s nothing left to pass – this is called tenesmus
- feeling extremely tired – either from the illness itself or lack of sleep, or from losing blood, which can cause anaemia
- losing your appetite
- losing weight
- feeling generally unwell
- a raised temperature
There’s a chance you could develop problems in other parts of your body too. For example, you might get:
- mouth ulcers
- skin rashes
- red or painful eyes
- painful, swollen joints
These problems usually occur during a flare-up, but can also happen while you’re in remission. You may feel anxious, and your symptoms can have a significant impact on your quality of life. For more information, see our section on living with ulcerative colitis.
If you have any of these symptoms, contact your GP for advice.
Diagnosis of ulcerative colitis
Your GP will ask about your symptoms and examine you. They’ll also ask about your medical history and if any other members of your family have bowel problems. They may ask you for a sample of poo (a stool sample) to check for bacterial infections in case your symptoms are due to an infection. This sample can also be used to look for a marker called faecal calprotectin. This marker can be raised if you have inflammatory bowel disease flare. They’ll ask you to have a blood test too.
Depending on the results, your GP may refer you to a gastroenterologist (a doctor who specialises in conditions that affect the digestive system).
You might need to have more tests, which can include the following.
- Colonoscopy. Your doctor will do this test to look at the lining of your large bowel to check for any ulcers or inflammation. They may take some samples of tissue (biopsies) from your bowel too. Your doctor may offer you pain relief to keep you as comfortable as possible.
- Flexible sigmoidoscopy. This test is similar to a colonoscopy, but it only looks at your rectum and the lower part of your large bowel. Your doctor can take biopsies during this test too.
- Gastroscopy. This involves putting a narrow tube (gastroscope) into your mouth and down your food pipe (oesophagus). It allows your doctor to look at the upper part of your digestive system. It can help your doctor to work out whether your symptoms may be due to Crohn’s disease or ulcerative colitis.
- CT or MRI scans. These will give detailed images of the inside of your body. They can help to show how much of your large bowel is affected by ulcerative colitis.
- X-ray. This may help to rule out serious problems like toxic megacolon (see our section on complications of ulcerative colitis).
Treatment of ulcerative colitis
Treatment for ulcerative colitis can control your symptoms and prevent flare-ups. The treatment you have will depend on how severe your ulcerative colitis is, and how much of your large bowel it affects. A team of healthcare professionals with specialist knowledge of inflammatory bowel diseases (your IBD team) will care for you.
Medicines
You may need to take different medicines when you’re in remission and when you’re having a flare-up. It’s important to keep taking your medicines, even if you feel well.
If you have a severe flare-up of ulcerative colitis, you may need to go into hospital urgently. You’ll need specialist care and intravenous medicines (these medicines are given directly into your vein).
Medicines for ulcerative colitis include the following.
Aminosalicylates
Aminosalicylates are also known as 5-ASAs and include mesalazine. You can take these as tablets or as a preparation that you put into your bottom (back passage). This can be a suppository (a dissolvable capsule you put up your bottom) or enema (a foam or liquid that you put up your bottom). You can take aminosalicylates during flare-ups and when you’re in remission, to help prevent symptoms.
Corticosteroids
Corticosteroids include hydrocortisone, prednisolone and budesonide. You may need to take these if aminosalicylates don’t control your symptoms when you have a flare-up or you can’t take aminosalicylates for some reason. You can take steroids as tablets or as a suppository or enema into your bottom. If you have a severe flare-up, you may have steroids intravenously (through a drip in a vein) in hospital.
Immunosuppressants
Immunosuppressants such as azathioprine and mercaptopurine work by calming down your immune system. Your doctor may prescribe these if you keep needing to take steroids for flare-ups or after a severe flare-up. You take these immunosuppressants as tablets.
Biological drugs
Biological drugs for ulcerative colitis include infliximab, adalimumab, ustekimumab, and vedolizumab. But your doctor may suggest these if you’re having flare-ups and other treatments aren’t working or you can’t take them for some reason. Biological drugs are usually given as injections – either into a vein or under your skin. Some, you take as tablets. If you get on well with them, you might continue taking them when you feel better, to prevent further flare-ups.
JAK inhibitors
Tofacitinib, filgotinib, and upadacitinib are JAK inhibitors. These block enzymes that your immune system uses to trigger inflammation. You can take them as tablets. You might need to take these if you have moderate to severe ulcerative colitis and other medicines haven’t worked or aren’t suitable for you.
Ozanimod
Ozanimod affects the way your immune system works. You take it as a tablet. You might need to take ozanimod if you have moderate to severe ulcerative colitis and other medicines haven’t worked or aren’t suitable for you.
If you have any questions about your medicines, ask a pharmacist or doctor. Let your doctor know if you’re trying to get pregnant because you shouldn’t take some of these medicines for ulcerative colitis if you’re pregnant.
Surgery
Surgery for ulcerative colitis is done as keyhole surgery wherever possible. It involves removing all or part of your large bowel. You may need surgery for reasons that include the following.
- You’re getting lots of flare-ups and medicines aren’t helping.
- You keep needing steroids to control your symptoms.
- Your doctor has identified changes in your bowel during check-ups for bowel cancer (see our section on complications of ulcerative colitis).
- You’re having a severe flare-up and you need surgery as an emergency treatment.
- You’d prefer to have surgery rather than keep taking medicines.
Around 10 in 100 people with ulcerative colitis have surgery within 10 years of being diagnosed. But this number is getting lower all the time as better treatments become available.
Surgery for ulcerative colitis often involves having an ileostomy. This means your surgeon will bring the end of your small bowel to open on the surface of your tummy (this is called a stoma). It’s a way for your body to get rid of waste products. You wear an ileostomy bag over the stoma, to collect the waste. You may need to have a temporary or a permanent ileostomy.
Your doctor will talk to you about what kind of operation is best for you and what’s involved. If you’re considering having surgery, it’s important that you discuss all the pros and cons with your doctor first. The most common types of surgery for ulcerative colitis are discussed here.
Pouch surgery
This is also called ileal pouch–anal anastomosis (IPAA) surgery. Your surgeon will remove your entire large bowel – both your colon and rectum. They’ll then make a pouch from the end of your small bowel, and stitch this to your anus. The pouch can store waste products and your poo can pass through your anus as normal. This operation is often done in two or three stages. You may need a temporary ileostomy while the new pouch heals.
Subtotal colectomy with ileostomy.
In this procedure, your surgeon will remove most of your large bowel but leave your rectum. You’ll need to have an ileostomy but this may not be permanent. Later on, you may be able to have pouch surgery.
Proctocolectomy with permanent ileostomy.
If you have a proctocolectomy, your surgeon will remove all of your large bowel, including your colon and rectum, and your anus. You’ll need a permanent ileostomy if you have this surgery.
GP Subscriptions – Access a GP whenever you need one for less than £20 per month
You can’t predict when you might want to see a GP, but you can be ready for when you do. Our GP subscriptions are available to anyone over 18 and give you peace of mind, with 15-minute appointments when it suits you at no extra cost.
Complications of ulcerative colitis
Ulcerative colitis can lead to a number of complications.
Toxic megacolon
Toxic megacolon is when your large bowel becomes enlarged and swollen as part of a severe flare-up. You’ll probably feel very unwell with a high temperature and tummy pain. It’s uncommon, but if you get these symptoms, seek urgent medical attention because you might need treatment in hospital.
Bowel cancer
Ulcerative colitis can increase your risk of getting bowel cancer. The risk is higher if you’ve had ulcerative colitis for a long time, if it’s not well-controlled, and if a lot of your bowel is affected. Your doctor may recommend you have regular colonoscopies to check for any signs of cancer. This will usually be from around 10 years after you first get symptoms. Keeping your colitis under control may help to reduce your risk of bowel cancer.
Perforation
Perforation (a tearing) of your bowel can be a complication of a severe flare-up. You might have severe pain, as well as a fever, nausea and vomiting. Seek urgent medical help if you develop these symptoms.
Anaemia
You may develop iron-deficiency anaemia if you have ulcerative colitis. The anaemia is caused by a lack of iron in your diet, poor absorption of iron from food or blood loss from your gut.
Vitamin deficiencies
If you have a poor appetite, don’t eat enough or have ongoing diarrhoea, you may develop a vitamin deficiency. You may need to take vitamin supplements.
Osteoporosis
If you have ulcerative colitis, you’re more at risk of developing thinner and weaker bones due to osteoporosis. This can happen because of ongoing inflammation, smoking, taking steroids or not exercising much. You may also not get enough calcium from your diet.
Ulcerative colitis is also linked to a health condition called primary sclerosing cholangitis. It affects your bile ducts (tubes that connect your liver and gallbladder to your small bowel). Primary sclerosing cholangitis causes your bile ducts to become more and more inflamed and damaged over time. You may need to take treatments to control your symptoms if you develop primary sclerosing cholangitis.
Living with ulcerative colitis
Ulcerative colitis is a life-long condition that can affect you physically and emotionally. Flare-ups can have a big impact on your social life, education, or work. But that doesn’t mean you can’t live life to the full.
Take care of yourself
It’s natural that living with ulcerative colitis can make you feel stressed at times. Stress can sometimes trigger flare-ups, so you may find it helpful to try some relaxation techniques. These include deep breathing, meditation, yoga and mindfulness.
If you take nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen, they may trigger ulcerative colitis. Instead, take alternative over-the-counter painkillers such as paracetamol.
Regular exercise can help to give you a boost and make you feel better. It can also improve your general health and help to keep your bones and muscles strong. This is important because if you have ulcerative colitis, you may be more at risk of osteoporosis .
You don’t have to eat a specific diet if you have ulcerative colitis but some foods may make your symptoms worse – for example, milk. Aim to eat a healthy balanced diet and keep a food diary to help you identify any problem foods. If you’re unintentionally losing weight or your doctor thinks you aren’t getting the nutrients you need, they may refer you to see a dietitian. You may need to take supplements of, for example, calcium and vitamin D to get everything you need.
Being prepared
Flare-ups can be unpredictable. To help prepare, make a flare-up plan with your doctor or nurse. This may involve adjusting the medicines you take, for instance.
If you feel anxious about going out, it can help to plan ahead. Find out where the nearest public toilets are. You may find it useful to carry a card to help tell people if you need to use the toilet urgently. If you’re worried about not getting to the toilet quickly enough, carry spare clothing in your bag so you can change. You may also want to carry moist wipes, and plastic bags for soiled clothes.
If you’re going on holiday, make sure you have enough medicine to take with you, including any you need for a flare-up. In case of delays, take extra medicines with you if possible and a doctor’s note to say what they’re for, especially if you’re flying.
Getting support
If you tell your family and friends about your condition and how it affects you, it may help them to give you the support you need. Your IBD team will also support you and there may be a helpline or email you can contact. Keep these to hand, and always seek advice as soon as you need it. Support groups, as well as online chat forums and message boards can offer a chance to talk to other people having similar experiences. See our section on other helpful websites.
How to improve your gut health
Gut health | Watch in 35:48 minutes
Watch our expert guide on boosting gut health, understanding food sensitivities, and managing everyday digestive symptoms.
Hello and welcome to Bupa's Inside Health series.
I'm Dr. Zoe Williams, and today we're going to be talking all about gut health.
What do we mean by gut health?
What things are good and bad for our gut, and what can we do to look after our gut health?
It's a really interesting topic, but it can be quite confusing, and a lot of the science is relatively new.
So I'm going to be joined by gut health dietitian Caitlin Colquhoun and Iona Bell, who's a specialist dietitian at Bupa Cromwell Hospital, to help us uncover this really interesting topic.
So Caitlin, let's start with: where is the gut, and what do we mean by gut health?
So gut health refers to the functioning of our entire gastrointestinal tract.
That's everything from our mouth all the way through to the exit at the other end.
Its main function is to absorb nutrients from the food that we eat and rid solid waste from the body.
It also hosts our gut microbiota—the community of trillions of bacteria which live inside our large intestine.
Now, for good gut health, there's no real universal definition, but I suppose it could be the absence of any unwanted gut symptoms like abdominal bloating, constipation, or diarrhea.
And when it comes to our gut health, that also influences other aspects of our health, which we'll come on to.
But what influences our gut health?
So the number one thing which influences our gut health is the food that we eat, in particular the dietary fiber we consume.
Dietary fiber forms the backbone of all of our plant-based foods: our fruits, our vegetables, our whole grains, our beans and lentils, and our nuts and our seeds.
Our gut microbes break down this fiber through a process known as fermentation, which produces all sorts of beneficial molecules which get sent all around the body.
We should be aiming for about 30 grams of fiber every single day, because this has been shown to reduce the risk of certain diseases such as heart disease and type 2 diabetes.
And we hear more and more now about the gut microbiome.
We also hear that the gut is the second brain and it somehow communicates with our brain and impacts our mental health, and it even affects our immune system.
So how is our gut having this huge influence on all these other parts of our health?
So our gut microbiome is not an organ in the conventional sense, but it's a community of trillions of bacteria, fungi, yeasts, and parasites which live in our large intestine.
Each microbe is capable of producing hundreds of chemicals which, as I was saying, get sent all around the body to help with our brain health, heart health, and skin health.
70% of our immune cells are found within the lining of our gut, which is why if we eat a healthy diet, we can help to support a healthy immune system.
That's fascinating to me to think that what we eat can impact all these various aspects.
Tell me a little bit more about the link between food and mood—so how what we eat can impact our mental health.
So 90% of our serotonin, known as our happy hormone, is actually produced within the gut, which is just another reason why it's so important to eat a diet rich in plant-based foods and dietary fiber to help improve our mental health.
And is it true that the opposite way is true—you can do things to look after your emotional health and that can give you better gut health?
Absolutely.
There's certain things you can do to help reconnect the gut and the brain, as it were.
Simple practices such as breathing, because breathing out helps to stimulate that rest-and-digest nervous system.
Another thing is meditation or mindfulness, because that can make you become very present and listen and tune in to what's going on inside the body.
One of my favorite practices is yoga, because as well as including the breathing and the meditation, yoga also involves movement like stretching and compression, which is almost like a little massage for your internal organs and for your gut.
So when it comes to a healthy diet, the guidance seems to change all the time.
The ideas change all the time, but if we're focusing on looking after our gut health, what suggestions would you have for a healthy diet?
So I suppose my top tips would be to try to eat a diverse range of plant-based foods.
That doesn't mean being 100% plant-based, but aiming for about 30 different plant-based foods per week.
The other thing is to avoid unnecessarily restrictive diets, so avoiding excluding any whole food groups unless you have a medical diagnosis to do so.
That means not completely cutting out carbs or cutting out fat, for example?
Exactly, and actually carbs are super important in our diet because they are so rich in dietary fiber.
The other thing is to try to eat the rainbow when it comes to different fruits and vegetables, because they all provide us with different antioxidants and polyphenols, which our gut microbes love.
And reducing our intake of these ultra-processed foods—so these are foods which contain things like artificial sweeteners, unknown ingredients, and are higher in fat and sugar.
And in addition to all of that, you can experiment with things like fermented foods.
So I'm talking sauerkraut, kimchi, kombucha, kefir, because we know, again, these are really beneficial for our gut microbes.
And we're going to be covering more of that a little bit later on as well.
So whilst it is natural then to focus on the foods we eat when we're talking about gut health, there are other parts of our life that are important as well, aren't there?
Like hydration and sleep.
Absolutely.
So I always say the most important thing is to chew your food really thoroughly, because I think we forget that digestion really does start in the mouth.
And the more we can chew our food, the easier it is for our body to absorb the nutrients from the food that we eat.
The other thing is to try to avoid wearing high-waisted, tight-fitted clothing, because the external abdominal pressure can sometimes worsen digestion and lead to things like abdominal bloating.
Trying to stop smoking and reduce your alcohol intake is really important, because smoking can decrease the diversity of the gut microbiome.
It's also important to remember to avoid taking unnecessary medications.
We all need to take medications from time to time, but especially things like the overuse of antibiotics.
Antibiotics, as well as killing off the bad bacteria, can often wipe out a lot of the good bacteria.
And the final thing is to really make sure we're drinking enough fluid every day, because we've talked about the importance of upping our dietary fiber, but fiber requires fluid to work effectively in the gut.
So we want to aim for two liters or eight glasses of water every single day.
Wow, so lots to think about, but I think for people, even if you make adjustments to just one or two of those things, then you're going to make improvements, aren't you?
Absolutely.
Thank you so much, Caitlin, for giving us that insight into the importance of our gut health and especially how it can impact our overall health.
So I'm now with Iona Bell, who's a specialist dietitian at Bupa's Cromwell Hospital, and we're going to be talking a little bit about gut health issues and touching upon food intolerances.
So Iona, as a specialist dietitian, tell me a little bit about your role and your day job.
So I currently work as a specialist dietitian at Cromwell Hospital.
So my mornings consist of ward rounds and also developing nutritional regimes for the patients on the critical care unit.
And so this is from IV nutrition to enteral feeding, which is where we insert a tube to feed directly into the gastrointestinal tract.
And my afternoons are spent in the outpatient clinics with the other specialist dietitians, and we see a wide variety of patients from IBS, inflammatory bowel disease, coeliac disease, diverticulitis, intolerances, and oncology cases, as well as many other clinical conditions.
So how might we know when something is potentially wrong with our gut?
What are the telltale signs and symptoms we should look out for?
So if you think that something might be wrong with your gut, you may notice symptoms such as constipation, diarrhea, flatulence, bloating, abdominal pain and cramps, and a general change in bowel habit.
But it's important to remember that these symptoms can be caused from a wide variety of conditions, and you may have one or two of the symptoms, or you may experience most, if not all, of them.
Okay, and I think all those things you mentioned, they're all things that we—I guess we'll get a little bit from time to time.
So when would you recommend is the right time to seek help—to go and see your GP, for example?
So you should see your GP if you think that anything is wrong with your gut, especially where symptoms are having an impact on your day-to-day life, and if you're noticing any blood in your stools, a change in stool consistency, or a change in stool color.
Your GP will then be able to help support you and also send you for some further tests.
Okay, so I guess based on that, you might get referred for some tests and you may even get a specific diagnosis.
And there are many different things that people might get sent to you for, aren't there?
What sort of types of things would you see?
Yeah, so we receive referrals for a variety of reasons through self-referrals or referrals through consultants and GPs.
And some of the most common referrals that we see are those for ulcerative colitis, Crohn's disease, coeliac disease, and IBS.
But we also receive referrals for general gut health......and also how to manage your intolerances and allergies.
So you mentioned IBS there, and I think that's probably one of the commonest conditions people think of when it comes to gut health.
But then there's also IBD, which is different.
Can you explain the difference?
Yeah, so inflammatory bowel disease is used to describe two conditions: Crohn's disease and ulcerative colitis, which both cause inflammation in the gut.
Crohn's disease affects any part of the gastrointestinal tract, from the mouth all the way to the anus, whereas ulcerative colitis only affects the large intestine.
If you think that you might have inflammatory bowel disease, you might notice symptoms such as blood in your stool, bloating, lethargy, weight loss, abdominal pain, cramps, and discomfort.
Generally, the symptoms of IBD will last for a period of time, which is what we call a flare-up, before going away.
It's really important if you think that you have IBD to speak with your GP, as they'll be able to help to offer you some advice as well as send you for some tests and treatment.
Irritable bowel syndrome, on the other hand, is a condition that affects the digestive tract, but there's no inflammation of the gut.
Symptoms can be quite similar to that of IBD—for example, you might get the bloating and the diarrhea.
Okay, great.
Thanks for explaining that.
And if people do get a diagnosis of a specific condition, is this then when they're likely to be referred to somebody like yourself, and you can look at diet and other potential causes of their symptoms and help them with a management plan?
Yes, we can help in a variety of ways.
For example, if someone comes to us who has IBS, we generally might ask them when their symptoms first started, and for some this can be during a really stressful period of time in their lives—for example, in their job, or it might be after a loss of a family member or close friend.
We will also take a diet history and also understand the symptoms that they're currently experiencing.
From there, we can give them first-line advice, which includes stress management, exercise, dietary advice, and also symptom control.
And if felt appropriate, we can give them the low FODMAP diet advice as well.
So you mentioned a low FODMAP diet.
Can you tell me a little bit more about that?
Yeah, so the term FODMAP is an acronym used to describe short-chain carbohydrates that are poorly absorbed in our small intestine.
FODMAP stands for fermentable oligosaccharides, disaccharides, monosaccharides, and polyols.
And these short-chain carbohydrates are poorly absorbed in everyone, but in those with IBS will cause them symptoms.
These FODMAPs are found in everyday foods—for example, in onions and garlic.
It's really important if you're going to go and do the low FODMAP diet that you speak with your dietitian, who can help advise you through the three stages.
This consists of complete elimination of these FODMAP foods from your diet, before bringing them back in one by one to see which cause symptoms and which you can tolerate.
And now a hotly debated topic in our recent Bupa customer survey was food intolerance.
Over 40% of customers responded said that they wanted to know more about it, so it's really a topic of great interest.
So I wanted to ask you a bit about that.
And firstly, what's the difference between food intolerance and food allergy?
So a food allergy is a reaction that involves the immune system.
It's where the body mistakes a protein that's found in food as a threat, and therefore a number of chemicals are released which cause the symptoms of the food allergy.
Almost any food can cause a food allergy, but the most common are nuts, eggs, fish, shellfish, some fruits and vegetables, and milk.
A food intolerance, on the other hand, does not involve the immune system.
And having a food intolerance can cause a wide variety of symptoms and reactions, but these can be very individual to you, with a delayed or immediate onset.
And what are the most common things in the diet that might cause a food intolerance or a food sensitivity?
So one of the most common food intolerances that we see is a lactose intolerance, and this is where someone might be able to tolerate a little bit of lactose in their diet or no lactose at all.
And we also see a non-coeliac gluten sensitivity, and this is where, despite someone not being diagnosed with coeliac disease or wheat allergy, still find that the gluten in food causes them some symptoms such as diarrhea, bloating, flatulence, and abdominal pain.
So would you say that more often than not it tends to be a case of food sensitivity rather than an intolerance?
Yeah, so for example, in someone who has IBS, they might find that having a tablespoon of onions does not cause them any symptoms, but having three tablespoons of onions causes them quite a lot of gut sensitivity and then brings on those symptoms.
It's the same, for example, someone with lactose sensitivity—that they can tolerate a lactose-containing yogurt, but having a lactose-containing cheese or milk causes them quite severe symptoms.
So what sort of symptoms might somebody get from a food intolerance or sensitivity?
Because they can present in all sorts of interesting ways, can't they?
Yeah, so if you've got a food intolerance or sensitivity, the symptoms of this are very individual to you, and they can present in a variety of ways.
However, some of the most common symptoms that we see is bloating, diarrhea, flatulence, and abdominal pain.
Some of the less common symptoms include heartburn, lethargy and tiredness, nausea, and acid regurgitation.
So if I suspect that I have an intolerance, should I go ahead and just start cutting things out of my diet and manage that myself, or do you think it's better to seek some advice from a healthcare professional?
So you should always see your GP if you think that something might be wrong with your gut and is causing you concern.
However, if you suspect that you have a food intolerance or sensitivity, you can by all means do this on your own and by doing the food elimination and reintroduction method.
So this involves taking that food that might be causing you symptoms, such as bloating, and removing it from the diet.
And then if the symptoms go away, you can then slowly reintroduce it back into the diet.
And if the symptoms return, then you know that this food is causing you problems.
It's important to do this if you can under the supervision of a dietitian, as they can help to ensure that your diet doesn't become too restrictive and it stays nutritionally complete.
Okay, so maybe if it's just the one particular type of food, have a go yourself.
But if there's loads of different things, you really need some help with.
Definitely.
Okay, and what if somebody wants to find out for sure?
A lot of my patients want to do a test.
They want to do a quick diagnostic test to find out if they have food intolerances.
Can they do that?
So unfortunately, unlike allergy testing, testing for food intolerances lacks validity.
There's lots of commercially available tests that you might have seen out on the market, and these tests tend to lack good evidence to back their claims.
An example of these tests: one is a hair analysis test, and this involves taking a strand of your hair and sending it off to the lab to test for food intolerances, but there's no scientific basis behind this and it lacks good evidence.
There's also IgG testing, which is where a sample of blood is sent away and it's tested for the IgG antibodies in the blood.
It's thought that an increase in these antibodies to certain foods shows an intolerance to that food.
However, it's been found that people who are healthy and have no symptoms at all have an increase in these antibodies as well, and it's thought that the foods that you might commonly eat might show up as an intolerance, so you might end up restricting unnecessarily.
There's also kinesiology testing, which is where muscle reactions are looked at when a food is placed near or next to the body.
However, there's no scientific basis behind this, and it's thought that the muscle reaction is no better than chance.
Okay, so I guess in summary, there's no simple test.
But if you're having symptoms, if they're persisting—particularly if you're having any symptoms you think could be IBD—it's definitely worth a trip to the GP to get some help and support.
Yeah, definitely.
Always go to your GP if you are struggling with anything or think there's anything wrong.
Iona, thank you so much.
That was really interesting and really useful, and really good to know that there's support out there to help people.
Now, all of this talk of food has made me think that it's time to unpack what is good and what is bad.
So I'm here in the kitchen with Caitlin, and I think it's probably fair to say that not a week goes by without a new health kick, new fad diet, new supposedly superfood—of which there is no such thing.
So it's really great to find out what is fact and what is fiction.
And I've got some foods here, some of which we probably tend to think of as good for us, and some of which we might think of as not so good for us.
So let's have a look at them.
But before we start with that, I wanted to ask you about probiotics.
So we see lots of probiotic supplements being marketed, but also probiotic drinks in the supermarkets now like kombucha and kefir.
So are they good for us, and should we be investing in them?
So really good question.
So you can find probiotics in foods that contain live beneficial bacteria, particularly our fermented foods—so things like kefir, kombucha, kimchi, or sauerkraut.
We have limited evidence to show their benefit, but lack of evidence doesn't equate to lack of benefit, and we have lots of ancestral evidence to show that these can be really beneficial for our health.
Those aren't to be mistaken with probiotic supplements, which you can buy in capsule form, or even some probiotic drinks.
And I just want to make it clear that a normal, healthy person does not need to take a probiotic to improve their gut health.
However, if you have a particular gut symptom you're trying to manage, then there might be a particular strain of probiotic bacteria which has been shown in the research to help manage that particular symptom.
Okay, good to know.
And what's the difference between a probiotic and a prebiotic?
So probiotics are the live, beneficial bacteria we can take to either maintain or improve our gut health, whereas prebiotics are the food for that gut bacteria.
And we can get prebiotics from different high-fiber foods in our diet—for example, things like onions and garlic, apples and pears, artichokes, beans, and lentils, just to name a few.
Okay, great.
Now one thing I wanted to ask you about, and I'm thinking about this plate over here, is what are the red flags when you're in a supermarket?
Because often packaging and marketing can be quite misleading and have us believe things are good for our health when actually they're maybe not so great.
Absolutely.
So it can be really confusing for a consumer to know what's good for our health and what's not.
And you want to be careful of products that are labeled as "natural" or even "vegan." That doesn't necessarily mean they're healthy for us.
So for example, if you pick up a packet, it's always good to look at the ingredients list.
You want to be able to understand and read all of the ingredients in the product.
There's a lot of ingredients on there—some things that I've never heard of before.
Absolutely.
So several ingredients, some of which you don't even know what they are.
So although this may look like a healthy choice, it may not be the most beneficial thing.
Whereas when you see other products—and this is a bar which contains just five ingredients—they're all whole, natural foods, and you therefore know this is a little bit better for your health.
So I guess there's no shortcuts.
You kind of have to look at the ingredients list and then make your own decision.
Yeah, absolutely.
One thing I wanted to ask about is caffeine.
So we've got some coffee, tea, and colas here.
Is caffeine really that bad for us?
So most people can consume up to 400 milligrams of caffeine a day—pregnant women just 200 milligrams.
How many cups is that?
So that would be about, depending on the strength of the tea or coffee, roughly four cups of tea or three cups of coffee, and you can consume that safely without any adverse side effects.
But caffeine is a stimulant and can worsen gut symptoms in those who are sensitive.
And it's all to do with how caffeine is metabolized in the gut.
And for people who are sensitive, impacts can include nervousness, anxiety, and insomnia, as caffeine can spike that stress hormone cortisol as well as cause these gut symptoms.
Okay.
Any health benefits to these?
Tea and coffee is rich in what we call polyphenols, and we know that polyphenols are really good for our gut health.
Any health benefits to these two, and is one worse than the other?
So things like fizzy drinks, they do contain caffeine, but they don't contain any other nutrition for our body in that sense.
Okay, so there's no real benefit to having them.
And what about artificial sweeteners?
Are they bad for our gut health?
There is evidence to show that high consumption of artificial sweeteners is detrimental to our gut health, so it's best to try to avoid them where you can.
Okay.
I've got some chilies here, so spicy foods.
Some people tend to think of these as triggers if you do have gut symptoms.
So are they good for us or not?
The active component in chili is known as capsaicin, and some people are affected by spicy foods whereas others are not.
And we tend to see those with increased gut sensitivity, such as those with IBS, become more sensitive to spicy foods.
Okay.
And what about alcohol?
Does that have a negative impact on our gut health?
So alcohol can increase the permeability of our gut, a term you may have heard be called "leaky gut," which can increase the sensitivity of the gut lining, especially in those with IBS.
Now, some people may be intolerant to certain components of alcoholic drinks, such as the gluten found in beer for people with coeliac disease, whereas others may react to the histamines or the sulfites found in different alcoholic products.
Some alcoholic drinks, for example red wine, do contain polyphenols, which we know can be beneficial for our gut health.
However, excess alcohol consumption isn't beneficial for our overall health, so it's important to try and reduce our intake where we can.
Okay.
Now this one I'm really interested in: chocolate.
Good or bad, and are all chocolates equal?
So the higher the percentage of cocoa, the more polyphenols and flavonoids it contains, which again can be really beneficial for our gut microbes.
However, we want to avoid overconsumption of any type of chocolate.
And especially the chocolates with the lower percentage of cocoa, they tend to be higher in fat and sugar, which we know isn't beneficial for our gut health.
Okay.
And I think with those sort of richer chocolate, you actually only need a small amount to feel satisfied, so doubly beneficial.
Here I've got some aubergines and tomatoes.
Although we know fruits and vegetables generally are very good for us, these are part of the nightshade family, and some people believe that the nightshade family can cause inflammation in the body.
Is there any truth in that?
So we have no evidence to show that nightshades can cause inflammation in the body.
And in fact, if we avoid all of these fruits and vegetables, we can be unnecessarily restricting the diversity of our diet, which we know is detrimental to our gut health.
When it comes to gut health, is it true that things like garlic, onions, and leeks are particularly good as prebiotics?
Absolutely.
They're really rich in these prebiotic fibers, as well as things like beans and lentils, artichokes, so they should definitely form part of a balanced diet.
And what about all the diets and crazes out there?
So juice cleanses, keto, Atkins—where do they stand when it comes to gut health?
So none of these diets have any evidence to show that they can be beneficial for our gut health.
In fact, they're all very low in dietary fiber, which we know is the most important thing when it comes to looking after our gut health.
People may feel temporarily better when they have a complete overhaul of their diet, but often these diets are unsustainable, and they're not providing our gut microbes with any goodness that they love.
I also wanted to mention about vegan diets, because people adopt a vegan diet assuming it equals a healthy diet, but that's not necessarily the case.
When we look at the premise of a vegan diet, it's to increase your intake of plant-based foods, which are rich in dietary fiber, which can increase the diversity of the gut microbiome.
However, you don't have to go completely vegan to improve your gut health, but focusing on a more plant-based diet, including some animal sources, can still have the same beneficial effect.
Thanks so much, Caitlin.
So I guess to wrap up, for people who don't have any conditions or intolerances, diet diversity really is the way to go alongside being active, looking after our mental health, and presumably the occasional treat is okay?
Absolutely.
Thank you so much, Caitlin.
That was so interesting.
Caitlin, I've read that fasting is beneficial for my gut and may ease my symptoms.
Is that true, and do the times that we eat affect our gut health?
It is recommended to avoid eating two to three hours before you go to bed because our digestive system does slow down at night, and this is especially true if you suffer from nocturnal reflux, which is reflux in the evening.
There is some evidence that giving your gut a rest—ideally 12 to 14 hours overnight—can be beneficial to allow specific microbes to essentially clean up the lining of your gut, which can keep it really healthy, which is really important to support a healthy immune system.
However, there's no need to skip meals, and typically an overnight fast is more than sufficient.
And it's actually recommended to try and eat a balanced meal every four hours during the day, so that would include your complex carbohydrates, your protein, and your healthy fats.
In some cases, it might be recommended to eat little and often, especially those who suffer from bad bloating or diarrhea, because smaller meal sizes can sometimes help to ease symptoms.
I think it's become quite popular to extend that fast.
A lot of people are aiming for around 18 hours a day, so there's no evidence that that's beneficial for gut health?
Not necessarily.
The evidence really lies more in people who are aiming to lose weight.
But with anything to do with the diet, it's not a one-size-fits-all.
This approach is really effective for some people, but not others.
Okay, thank you.
Iona, question for you: I regularly get heartburn after eating.
How can I make it stop?
So if you regularly get heartburn after eating, it's really important to speak to your GP, and they might be able to prescribe you some medications to help with the symptoms.
There are some dietary foods that have been found to aggravate symptoms.
These are spicy foods, fatty foods, caffeinated drinks, tomato products, and also your citrus fruits and juices.
And it might be recommended to try and reduce your consumption of these or eliminate them from the diet.
It's also advised to try not eat two to three hours before you go to bed, and also make sure you're following a healthy, balanced diet.
Okie-dokie.
Caitlin, should I avoid antibiotics?
Will it make my gut health worse?
Now look, we all become ill at times when antibiotics really are a necessity.
But avoiding antibiotics unless absolutely necessary leaves the healthy gut bacteria from being wiped out and causing long-term changes to the gut microbiota.
In terms of the evidence for if we do take antibiotics, there is some evidence that actually taking probiotics can help to prevent antibiotic-associated diarrhea.
So it'd be recommended to take them for the duration of the antibiotic course and for two weeks afterwards.
And would it be just specific patient groups that that would be recommended for, or anyone who's taking antibiotics?
Anyone in particular who's taking an antibiotic could benefit from taking a probiotic.
Okay, all right.
That's good to know.
Next question: what causes Crohn's disease?
That's one for you, Iona.
So the prevalence of Crohn's disease is increasing worldwide, but the exact cause of Crohn's disease still remains unknown.
There are some risk factors that have been found to maybe increase your prevalence of Crohn's disease.
For example, it's more likely to be diagnosed in your adolescence and younger adults, as well as your genetics can play a role.
And so if someone in your family is diagnosed with Crohn's disease, you also then have an increased chance of getting Crohn's disease.
And there's also some other factors—for example, your environment and your ethnicity.
I would like to point out, though, that food and stress, although they can aggravate symptoms, these have not been found to actually be a cause of Crohn's disease.
So it has been shown for IBS to run in families.
So if people haven't discussed their gut symptoms with their family, then I always encourage them to do so because they might not be the only ones suffering alone.
But relatives of an individual with IBS are two to three times more likely to have IBS.
However, studies have shown that individuals may develop IBS sporadically, meaning no one else in the family necessarily suffers from IBS.
And I guess the thing with things running in families is the genetics that connect the family, but often people in the same family have similar environmental risks as well, don't they?
So it can be difficult to unpick why—what the reasons are exactly.
Okay, question for you, Iona: what would you recommend to cure repeated constipation?
So if you're struggling with constipation, it is important that you speak with your GP, and they might be able to prescribe you some laxatives or there might be another problem that they can help diagnose you with.
But there are some dietary changes that you can make.
And one is making sure that you've got enough fiber in your diet so you're getting the recommended 30 grams of fiber a day, and so this is found in your fruits and vegetables and also your wholemeal products.
It's also important that you're staying hydrated, having the recommended six to eight glasses of water per day, and also exercising if you're able to.
So a normal frequency of bowel movement tends to be between one to three stools a day.
If you find that you're outside of your normal habit and you're not going as regularly as you maybe once were, then that's when you maybe want to start speaking to your GP.
Absolutely.
So we see differing gut symptoms at different times of the menstrual cycle due to the change in hormones.
So during menstruation, aka the period, you get an increase in this hormone-like chemical called prostaglandin.
The role of prostaglandin is to get the lining of the uterus to contract, but that effect doesn't just stay in the uterus, and it can also have an effect on the bowel, which causes an increase of movement of food through the digestive system, which leads to looser and more frequent poops.
On the flip side, during the luteal phase of menstruation, we get an increase in the hormone known as progesterone, and this can actually slow down the rate of motility through the digestive system, leading to things like constipation.
Okay, that's really interesting.
Thank you.
And then my final question is another one for you, Iona: what causes wind?
How much is too much?
Is there a certain point in which we need to be alarmed, and does it differ from person to person?
So wind is perfectly normal, and it's produced as part of our digestive process when the foods that we eat are fermented in our large intestine.
In some conditions, for example IBS, people might find that they produce more wind after eating certain foods than what they normally would.
In terms of wind, how much someone produces is very individual to them.
So if you find that you're producing more than normal, then it's important to go and speak to your GP just in case there's something else going on.
So I think it's kind of like with a lot of things, isn't it?
What's normal is quite a wide variety, but if there's a real significant change from what your normal is, that's when you should seek some help and advice.
Exactly.
Well, that's it.
I'm afraid that's all we have time for today, so thank you both so much for joining me.
If anything we've talked about today has got you thinking about your own gut health—maybe there's an issue you've been having or something you'd like to get checked out—there's much more information on the Bupa website, or do make an appointment to see your own GP.
If you take nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen, they may trigger ulcerative colitis. Instead, take alternative over-the-counter painkillers such as paracetamol. Other things that can trigger ulcerative colitis include an infection in your gut.
For more information, see our sections on causes of ulcerative colitis and living with ulcerative colitis.
The only cure for ulcerative colitis is surgery to remove all of your large bowel. But there are many treatments available that can help to keep your symptoms under control and these may be enough for you.
For more information, see our section on treatment of ulcerative colitis.
Your risk of developing ulcerative colitis is higher if a close family member has it. But having a family member with ulcerative colitis doesn’t mean you’ll definitely get it. Ulcerative colitis is likely to be caused by a combination of things, and genetics is just one potential cause.
For more information, see our section on causes of ulcerative colitis.
Ulcerative colitis can often come on very slowly and gradually. You might notice bleeding and passing mucus from your bottom first. You may have diarrhoea and pains in your tummy too.
For more information, see our section on symptoms of ulcerative colitis.
Other helpful websites
Discover other helpful health information websites.
Did our Ulcerative colitis information help you?
We’d love to hear what you think. Our short survey takes just a few minutes to complete and helps us to keep improving our health information.
The health information on this page is intended for informational purposes only. We do not endorse any commercial products, or include Bupa's fees for treatments and/or services. For more information about prices visit: www.bupa.co.uk/health/payg
This information was published by Bupa's Health Content Team and is based on reputable sources of medical evidence. It has been reviewed by appropriate medical or clinical professionals and deemed accurate on the date of review. Photos are only for illustrative purposes and do not reflect every presentation of a condition.
Any information about a treatment or procedure is generic, and does not necessarily describe that treatment or procedure as delivered by Bupa or its associated providers.
The information contained on this page and in any third party websites referred to on this page is not intended nor implied to be a substitute for professional medical advice nor is it intended to be for medical diagnosis or treatment. Third party websites are not owned or controlled by Bupa and any individual may be able to access and post messages on them. Bupa is not responsible for the content or availability of these third party websites. We do not accept advertising on this page.
- Lynch WD, Hsu R. Ulcerative colitis. StatPearls Publishing. www.ncbi.nlm.nih.gov/books, last updated 5 June 2023
- Ulcerative colitis. NICE Clinical Knowledge Summaries. cks.nice.org.uk, last revised April 2020
- Ulcerative colitis. NICE British National Formulary. bnf.nice.org.uk, last updated 1 November 2023
- Ulcerative colitis. BMJ Best Practice. bestpractice.bmj.com, last reviewed 3 October 2023
- Ulcerative colitis. Your guide. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed May 2021
- Flare-ups. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed August 2023
- Tests and investigations. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed September 2022
- Biologics and other targeted medicines. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed July 2023
- Infliximab. NICE British National Formulary. bnf.nice.org.uk, last updated 1 November 2023
- Infliximab. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed November 2020
- Tofacitinib. NICE British National Formulary. bnf.nice.org.uk, last updated 1 November 2023
- Filgotinib for treating moderately to severely active ulcerative colitis. National Institute for Health and Care Excellence (NICE). www.nice.org.uk, published 1 June 2022
- Ozanimod for treating moderately to severely active ulcerative colitis. National Institute for Health and Care Excellence (NICE). www.nice.org.uk, published 5 October 2022
- Ozanimod. NICE British National Formulary. bnf.nice.org.uk, last updated 1 November 2023
- Surgery for ulcerative colitis. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed October 2022
- Ulcerative colitis. MSD Manuals. msdmanuals.com, reviewed/revised January 2022
- Colorectal cancer prevention: Colonoscopic surveillance in adults with ulcerative colitis, Crohn's disease or adenomas. National Institute for Health and Care Excellence (NICE). www.nice.org.uk, last updated 20 September 2022
- Bowel cancer risk. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed April 2019
- Primary sclerosing cholangitis. BMJ Best Practice. bestpractice.bmj.com, last reviewed 6 October 2023
- Mental health and wellbeing. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed June 2020
- Food. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed February 2023
- Travelling with Crohn's or colitis. Crohn's and Colitis UK. crohnsandcolitis.org.uk, last reviewed June 2022

 Member help and support


